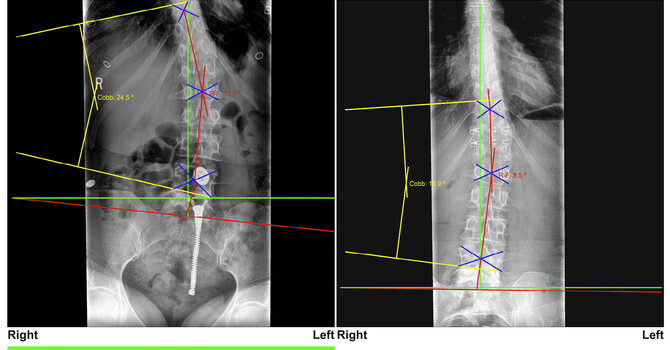
Families searching for a way to avoid spinal fusion tend to run into two extremes online: pages that treat fusion as inevitable once a curve crosses some threshold, and pages that promise a proprietary program will prevent surgery without showing the data behind that claim. Neither is a fair representation of where the evidence actually sits. This page lays out, in order, when fusion is genuinely indicated, what the published bracing trial data shows, and what conservative corrective care can and cannot claim for itself, including my own.
When Is Fusion Actually Recommended?
Spinal fusion is generally discussed once a curve reaches roughly 45 to 50 degrees Cobb angle in a skeletally immature patient, or when a curve of that magnitude continues to progress in an adult. Below that range, in the 20 to 40 degree window, the standard of care shifts toward bracing and monitoring rather than surgery, provided the patient still has significant growth remaining. Curves under 25 degrees in a growing child are typically observed, not braced or operated on, unless progression is documented on serial films.
This matters because a lot of the anxiety driving people to search for fusion alternatives applies to curves that were never headed toward surgery in the first place. The first job of an evaluation is establishing where a given curve actually sits on that spectrum, not assuming the worst-case pathway.
What the Bracing Evidence Actually Shows
The strongest evidence available on preventing surgery in adolescent idiopathic scoliosis (AIS) is the BrAIST trial (Weinstein SL, Dolan LA, Wright JG, Dobbs MB. Effects of Bracing in Adolescents with Idiopathic Scoliosis. N Engl J Med. 2013;369:1512-1521). It enrolled patients with curves in the 20 to 40 degree range and Risser sign 0 to 2, using a combined randomized and preference cohort. The trial was stopped early because the bracing benefit was large enough to be conclusive: 72 percent of braced patients reached skeletal maturity without progressing to the 50 degree surgical threshold, compared to 48 percent in the observation group. The effect was dose-dependent. Patients wearing the brace more than 13 hours a day reached success rates in the 90 to 93 percent range.
That is a genuinely strong result, and it is the single most defensible answer to "how do I avoid fusion" for a growing adolescent with a moderate curve: brace, and wear it as prescribed. It is also a randomized trial, which is a higher evidence tier than almost anything else in the conservative scoliosis literature, including my own published work discussed below. Any conversation about avoiding surgery should start here, not with a proprietary program's internal numbers.
What Conservative Corrective Care Adds, and Where the Evidence Is Weaker
Beyond bracing, corrective approaches under the CLEAR Institute protocol combine scoliosis-specific exercise, postural rehabilitation, and, in some cases, corrective bracing aimed at active curve reduction rather than curve-holding alone. I have published case-level work in this area, and I want to be direct about what that evidence tier can and cannot support.
- A published 13-month case study documented measurable curve reduction in AIS using this protocol. That is meaningful for the individual case, but a single case does not establish a population-level success rate.
- A case series applying an intensive two-week CLEAR Institute protocol to a Lenke 5C curve pattern documented outcomes in two patients. Again, informative, not generalizable.
- Work on the labyrinthine righting reflex and its relationship to AIS reduction outlines a plausible mechanism, not a proven one at trial level.
If you see a program anywhere, mine included, cite a single headline success percentage (a "93% success rate" is a common example in this space) without a published, peer-reviewed methodology behind it, that number deserves the same scrutiny you'd apply to a drug ad. Case reports and case series are the right evidence tier to generate hypotheses and document what is clinically possible in a specific patient. They are the wrong evidence tier to promise an outcome to a family walking in the door.
How Bracing and Corrective Care Compare
| Approach | Evidence tier | What it claims |
|---|---|---|
| TLSO bracing (BrAIST protocol) | Randomized/preference cohort trial, NEJM 2013 | Reduces progression to the 50° surgical threshold in 20–40° curves, dose-dependent on wear time |
| CLEAR-protocol corrective care (published case work) | Case study / case series, Cureus | Documented curve reduction in specific individual cases; mechanism-plausible, not population-proven |
| Proprietary programs citing an internal success percentage with no published methodology | Not independently verifiable | Marketing claim, treat with the same skepticism as any unpublished statistic |
What an Evaluation at Clear Life Looks Like
- Baseline imaging and Cobb angle measurement — establishing where the curve actually sits relative to the bracing and surgical thresholds above.
- Skeletal maturity assessment — Risser sign and growth remaining, since that changes which interventions are even relevant.
- Honest evidence discussion — if bracing is indicated per BrAIST criteria, that gets said plainly. If corrective exercise and postural rehab are added, the case-level nature of that evidence gets said plainly too.
- A documented plan with re-imaging intervals — progression is tracked on film, not assumed from how someone looks or feels.
Research and Evidence
- Weinstein SL, Dolan LA, Wright JG, Dobbs MB. Effects of Bracing in Adolescents with Idiopathic Scoliosis. N Engl J Med. 2013;369:1512-1521. (Randomized/preference cohort trial, not authored by Dr. Dick, cited as the governing bracing evidence.)
- Long-Term Scoliosis Correction — Dick JM. 13-month case study documenting AIS curve reduction under the CLEAR protocol.
- A Non-Surgical Multimodal Approach to AIS (Lenke 5C) — case report of two patients under an intensive two-week CLEAR Institute protocol.
- Reduction of AIS Utilizing the Labyrinthine Righting Reflex — mechanistic case-level work on a proposed neurological driver of curve reduction.
Full list at the research and publications page.
Frequently Asked Questions
What Cobb angle requires spinal fusion?
Fusion is generally discussed once a curve reaches roughly 45 to 50 degrees in a skeletally immature patient and continues to progress, or in an adult with a curve of that magnitude causing functional decline. Curves below that range are typically managed with bracing or observation.
Does bracing actually prevent scoliosis surgery?
Yes, for the population studied. The BrAIST trial (NEJM, 2013) found 72 percent of braced adolescents with 20 to 40 degree curves avoided progression to the surgical threshold, versus 48 percent with observation alone, with better results the more hours the brace was worn.
Can exercise or chiropractic care reduce a scoliosis curve without surgery?
Case-level published work, including studies from Dr. Justin Dick, DC in Charlotte, NC, has documented measurable curve reduction in individual patients using scoliosis-specific corrective exercise and postural rehabilitation. This evidence tier supports that reduction is clinically possible in some patients; it does not establish a guaranteed population-wide success rate.
Is a program's advertised "success rate" for avoiding scoliosis surgery reliable?
Only if it comes from a peer-reviewed, published methodology you can actually read. An unpublished internal percentage should be treated the same way you'd treat any unverified marketing statistic, useful as a lead, not as evidence.
What happens if a curve is observed instead of braced or treated?
Observation means serial imaging at set intervals, typically every 4 to 6 months during active growth, to catch progression early. It is appropriate for smaller curves without documented progression, not a default for every case.
What makes Clear Life Scoliosis and Chiropractic Center's approach to this question different?
Dr. Justin Dick, DC is a CLEAR Scoliosis Institute Fellow and Board member with published, PubMed-indexed case work on AIS reduction, and this page states plainly where that evidence is strong (bracing, per BrAIST) and where it is still case-level (his own corrective care research), rather than presenting either as more settled than it is.
Service Area
Clear Life Scoliosis and Chiropractic Center evaluates scoliosis patients from Charlotte NC, Huntersville NC, Ballantyne NC, Matthews NC, Concord NC, Mooresville NC, Rock Hill SC, and Fort Mill SC.
Related Pages
- About Scoliosis
- Treatment Options
- Bracing for Scoliosis
- Scoliosis Care Program
- Research and Evidence
- Dr. Justin Dick Research and Publications
- Questions and Answers
- ScoliBrace in Charlotte
- SpineCor in Charlotte
- Our Team
- Book Your Evaluation
Clear Life Scoliosis and Chiropractic Center
8814 Rachel Freeman Way, Suite 103, Charlotte, NC 28278
Phone: 980-368-0766 · clearlifescoliosis.com
Justin Dick
Contact Me